September 29, 2026
SuperPATH Hip Replacement and Thyroid Disease: Pre-Op Plan
Thyroid disease doesn't automatically rule out hip replacement, but an old diagnosis alone can't tell your surgical team whether you're ready. If you're considering SuperPATH hip replacement , your current thyroid function, symptoms, medications, and overall health all matter before a date is set.
The goal is a plan that accounts for both your hip and your thyroid condition. That starts with a clear picture of what SuperPATH changes, and what it doesn't.
How SuperPATH hip replacement fits into thyroid care
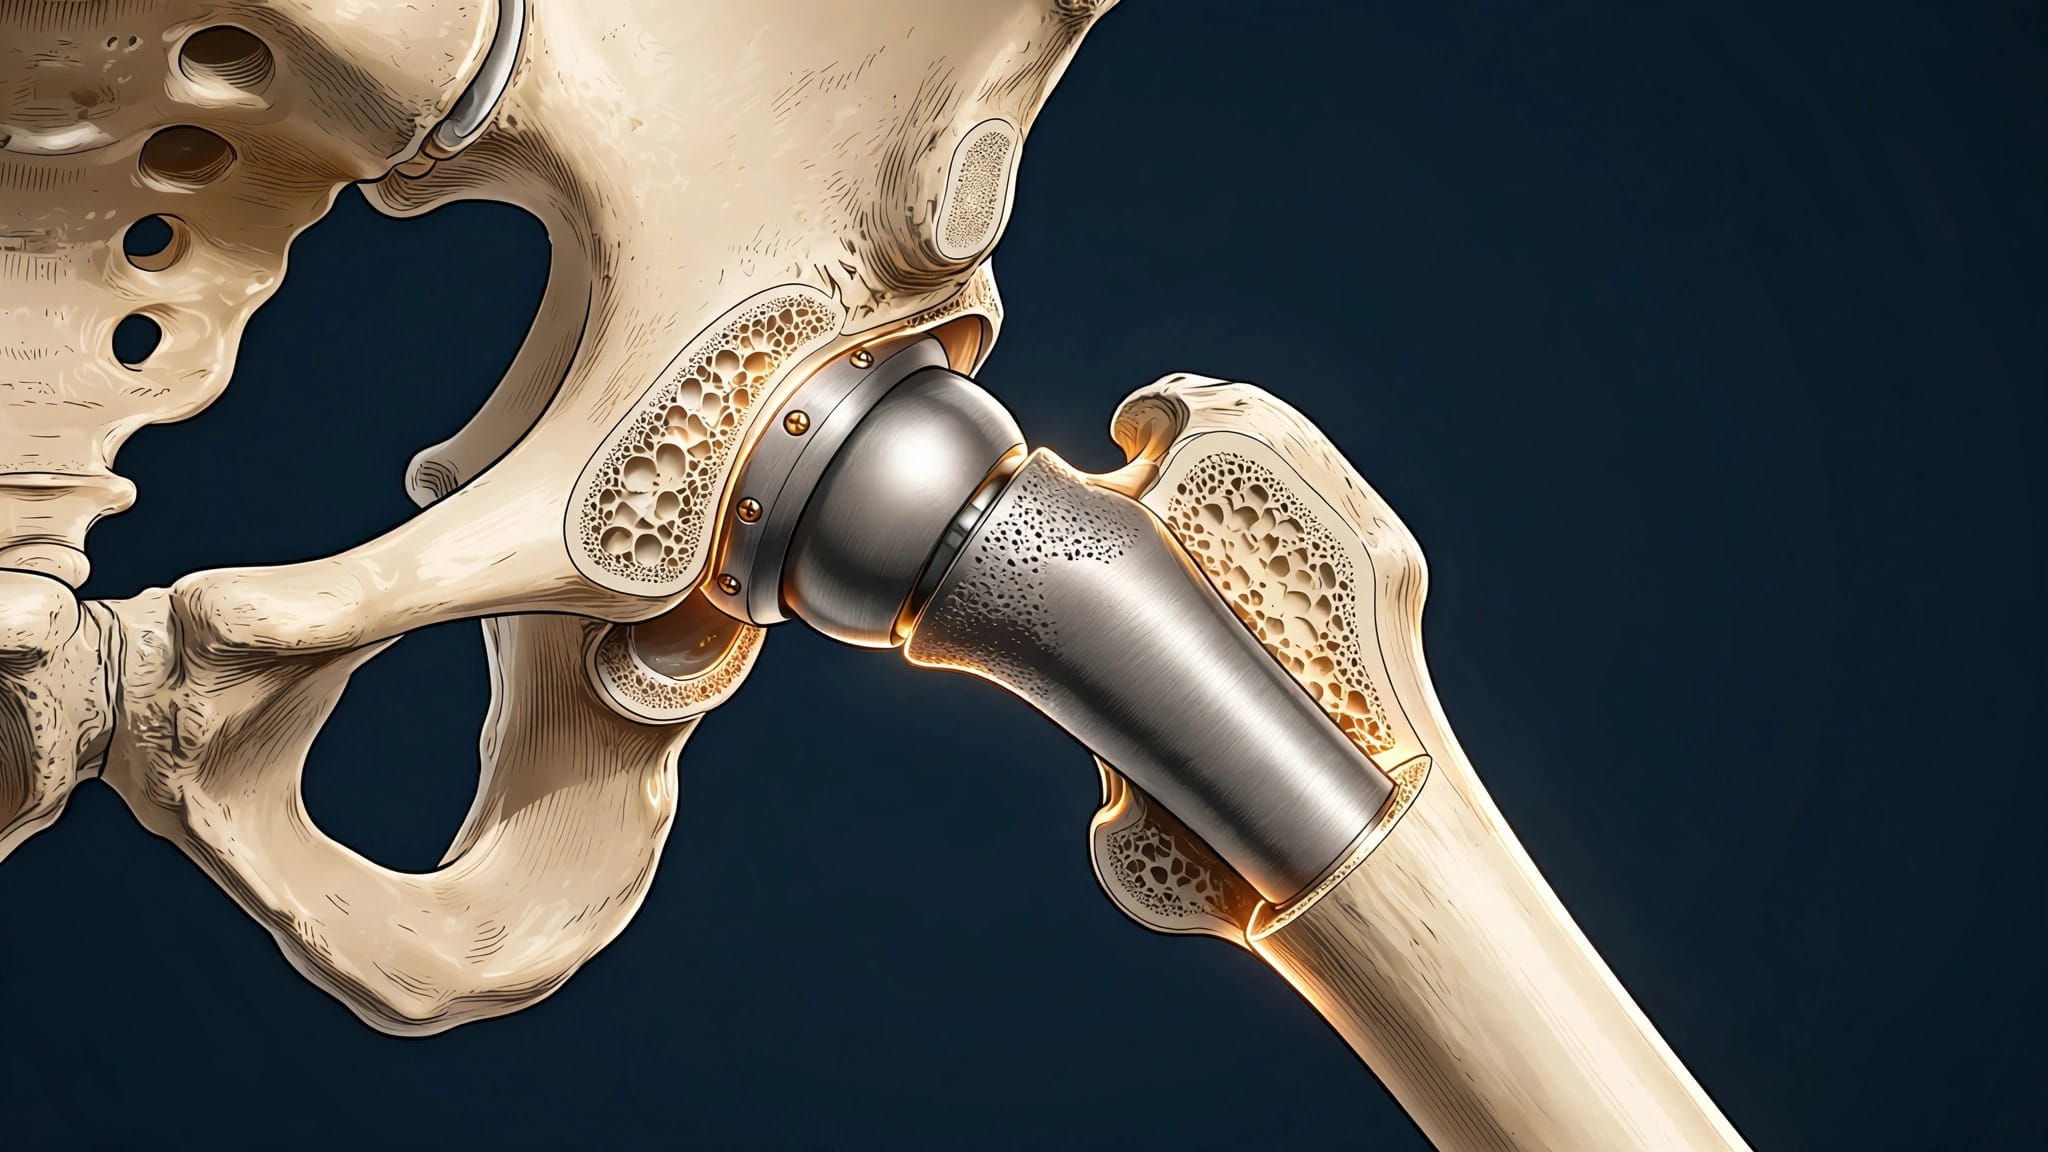
SuperPATH is a tissue-sparing approach to total hip replacement. The surgeon reaches the joint while working to limit disruption to surrounding muscles and tendons. Some patients may move comfortably early in recovery, but the approach doesn't guarantee less pain or a faster return to daily activities.
It's still a major operation that requires anesthesia, implant placement, wound healing, and rehabilitation. Thyroid disease affects the medical preparation , rather than creating a separate version of the SuperPATH procedure. Your surgeon must also decide whether the approach fits your hip anatomy, bone quality, and surgical history.
Well-controlled thyroid disease may require little change beyond confirming your results and medication plan. Active symptoms or abnormal thyroid levels may call for more evaluation before elective surgery. The difference depends on what condition you have and how you're doing now.
Which thyroid details matter before surgery?
"Thyroid disease" can mean an underactive thyroid, an overactive thyroid, or a condition treated in the past. Those histories don't carry the same questions for anesthesia and recovery.
Bring your diagnosis and recent results
Tell the team whether you have hypothyroidism, Graves' disease, thyroid nodules, or a history of thyroid surgery or radioactive iodine treatment. Bring recent thyroid test results if you have them. A thyroid-stimulating hormone test (TSH) is often part of the review; your treating clinician may also use free T4 or other tests.
A single result needs context. For example, some people treated for thyroid cancer have an intentionally low TSH. Your treating clinician can explain what your result means for you rather than leaving the surgical team to interpret it alone.
Describe symptoms, not only lab numbers
Report new fatigue, unusual cold or heat intolerance, tremor, palpitations, or an unexplained change in weight. Tell the anesthesiologist about a large goiter, trouble swallowing, or any breathing symptoms, too.
Your orthopedic surgeon, anesthesiologist, and thyroid-treating clinician each need the same current information. A preoperative health review before SuperPATH surgery helps identify which issues need attention before you arrive at the surgical center.
Hypothyroidism: when does it change the schedule?
If your thyroid makes too little hormone, the team will want to know whether treatment is working. The answer matters more than the diagnosis by itself.
Controlled hypothyroidism may need a straightforward plan
Many people take levothyroxine and have stable thyroid function. In that situation, the team may review a recent TSH result, ask about symptoms, and confirm how you'll take your medication around surgery. A thyroid diagnosis alone doesn't mean you must postpone your hip replacement.
If your dose recently changed, let your treating clinician know about the planned operation. Ask whether your latest test reflects your current treatment. There isn't one universal testing date or lab cutoff that determines readiness for every patient.
More severe disease needs closer review
With overt or severe hypothyroidism, clinicians generally prefer to improve thyroid function before elective surgery. Untreated severe disease can affect heart and breathing function, body temperature, and responses to anesthesia. Myxedema coma is rare but serious.
Mild or subclinical hypothyroidism is a different situation. An abnormal TSH with a normal free T4 doesn't automatically lead to the same decision as severe disease. Your clinicians will consider your symptoms, other health conditions, and the reason for your test result before deciding whether surgery can proceed.
Hyperthyroidism: why might elective surgery wait?
An overactive thyroid can place extra strain on the heart. Preparation focuses on whether thyroid hormone levels and symptoms are under control, not simply whether you have an established diagnosis.
Overt hyperthyroidism raises anesthesia concerns
Uncontrolled hyperthyroidism may cause a fast heart rate or an irregular rhythm. Surgery can also place stress on the body; in someone with overt thyrotoxicosis, a rare but dangerous thyroid storm is a concern. For elective hip replacement, clinicians generally recommend treating overt hyperthyroidism until the patient is clinically and biochemically stable.
That doesn't mean everyone with a low TSH needs the same delay. Subclinical hyperthyroidism and an intentionally suppressed TSH require individual interpretation. Your treating clinician should explain your results and treatment goals to the surgical and anesthesia teams.
Treatment may take time to assess
Depending on your condition, treatment may involve an antithyroid medicine such as methimazole or propylthiouracil (PTU). Some patients also take a beta blocker, such as propranolol, to control symptoms. These drugs have different purposes, so don't change either one based on a surgery date alone.
If treatment has recently started or changed, ask who will order follow-up tests and tell the surgeon when the results are ready. Your care team, rather than a fixed waiting period, should decide when your condition supports elective surgery.
Make one medication plan everyone can follow
Medication instructions can differ between patients and surgical facilities. Get directions for each prescription instead of assuming all thyroid medicines follow the same rule.
Confirm thyroid medicine timing
People whose hypothyroidism is controlled with levothyroxine are generally advised to continue treatment around surgery. Still, ask exactly what to take on the morning of your procedure and whether a sip of water is allowed under your facility's instructions.
If you take an antithyroid medicine, a beta blocker, or both, ask who will manage them before surgery and when you'll resume your usual schedule afterward. Don't stop, skip, or change a dose unless your care team directs you to. Bring the name, dose, and usual time for every medicine you take.
Include the rest of your medication list
Blood thinners, corticosteroids, diabetes medicines, over-the-counter products, and supplements can also affect surgical planning. Include allergies and any previous reaction to anesthesia. Your team can give you written directions after reviewing the complete list.
For questions beyond thyroid treatment, use the practice's guide to medication timing before SuperPATH surgery as a starting point for discussion, then follow your personal instructions.
Who decides whether you're ready for SuperPATH?
Thyroid clearance and hip-surgery candidacy are related decisions, but they answer different questions. Your treating clinician can assess thyroid control. Your surgeon must still decide whether replacing the joint, and using the SuperPATH approach, makes sense for your hip.
Your surgeon evaluates the hip
An in-person exam and imaging help show the shape of the joint, bone loss, leg-length differences, and any previous hardware. Severe deformity or prior surgery may make another approach more suitable. Pain level and age alone can't settle that choice.
Share how far you can walk, whether you use a cane or walker, and what you hope to do after recovery. Those details help your surgeon plan for safe movement after the operation, not only for the operation itself.
Your medical team reviews the whole picture
Your primary care clinician or thyroid specialist may review thyroid testing and other conditions, such as heart disease or diabetes. Meanwhile, the anesthesiologist considers your symptoms, medicines, airway, and anesthesia options.
Ask which clinician will confirm that your thyroid plan is complete and who will communicate changes to the surgeon. If a result is still pending, don't assume silence means clearance. Make sure you know whether it could affect your surgery date.
What changes in anesthesia and early recovery?
Thyroid control can affect anesthesia planning even when the surgical approach stays the same. An underactive thyroid may alter how someone responds to medications and temperature changes. An overactive thyroid can raise concerns about heart rate and rhythm.
Discuss anesthesia before the day of surgery
Tell your anesthesiologist about recent thyroid symptoms, dose changes, heart palpitations, and any neck swelling or trouble breathing. Also mention sleep apnea, prior anesthesia problems, and medicines you take for heart or thyroid symptoms.
The choice of spinal or general anesthesia depends on more than the SuperPATH name. Reviewing anesthesia options for SuperPATH hip replacement can help you prepare questions, but your anesthesiologist will recommend a plan based on your health.
Plan support without assuming a fixed timeline
Some patients walk with an assistive device soon after hip replacement. Others need more help with balance, pain, or fatigue. Thyroid symptoms, other health conditions, and your mobility before surgery may influence the support you need.
Ask your surgeon when you can bear weight and which movements to avoid. Your physical therapist can then work with you on walking, transfers, and a safe return to daily tasks.
Prepare for the final days before surgery
Keep your thyroid results, medication list, and clinician contact details together. At your final visit, confirm which tests are complete, who will contact you about an abnormal result, and which medicines to take on surgery morning. Follow your facility's instructions for food, drink, and arrival time.
Tell the surgical team promptly if you develop new palpitations, marked weakness, fever, or another significant change in health. An illness, skin problem, or new breathing symptom also deserves a call before the procedure. Don't wait until check-in to mention it.
At home, clear walking routes, remove loose rugs, and arrange help with transportation and meals. Keep frequently used items within easy reach. If you're unsure how the day will unfold, the practice's SuperPATH surgery day guide describes check-in and preoperative preparation.
Key Takeaways
- Thyroid disease alone doesn't rule out SuperPATH; current thyroid control and overall health shape the plan.
- Controlled hypothyroidism may require medication and test review, while overt or severe disease can call for treatment before elective surgery.
- Overt hyperthyroidism generally needs control before elective surgery because of heart and thyroid-storm risks.
- Confirm medication timing with your care team, and make sure your surgeon, anesthesiologist, and treating clinician share the same information.
Frequently Asked Questions
Can I have SuperPATH hip replacement if I take levothyroxine?
Often, yes. Taking levothyroxine doesn't by itself prevent hip replacement. Your team will look at your current thyroid function, symptoms, dose history, and other health conditions. Ask for personal instructions about taking your medicine on surgery morning rather than adjusting it yourself.
Does an abnormal TSH automatically cancel surgery?
No single result answers that question on its own. A clinician may need to consider free T4, symptoms, recent medication changes, and why your TSH is outside the usual range. Overt, uncontrolled thyroid disease generally calls for more caution before elective surgery than a mild or subclinical finding.
Will SuperPATH reduce the risks of uncontrolled thyroid disease?
The tissue-sparing approach doesn't remove thyroid-related anesthesia or heart concerns. If your thyroid condition needs treatment first, changing the hip-replacement approach doesn't replace that preparation. Your surgeon and medical team can discuss both decisions with you before setting a date.
A plan built around your current health
Thyroid disease changes preparation most when your current function is uncertain or your symptoms are active. Clear results, medication instructions, and communication among your clinicians give everyone a better basis for deciding when to proceed.
A hip approach can be chosen only after your surgeon evaluates your joint. Surgery readiness also depends on the health you bring into the operating room.
ADDITIONAL ARTICLES