September 30, 2026
Chronic Opioid Use Before SuperPATH: Your Pain Plan
If you already take opioids regularly, it's reasonable to wonder whether pain medicine will still work after hip replacement. Chronic opioid use can change your response to medication, but it doesn't automatically rule out SuperPATH surgery.
The safest preparation is an individualized plan shared by your surgeon, anesthesiologist, and opioid prescriber. SuperPATH's muscle-sparing approach doesn't guarantee opioid-free recovery or remove the need for careful monitoring.
Start by making sure everyone understands what you take, why you take it, and how your medication will be managed before and after surgery.
How Chronic Opioid Use Changes Pain Planning
Long-term opioid treatment can affect both pain relief and medication safety. Your team needs to plan for your usual pain condition as well as the temporary pain caused by surgery.
Tolerance and physical dependence
With repeated opioid exposure, your body may develop tolerance. That means a dose that once helped may provide less relief. After surgery, some patients need more pain medication than people who haven't been taking opioids.
Physical dependence means your body has adapted to the medication. Abruptly stopping it can cause withdrawal, including sweating, diarrhea, restlessness, and worsening pain. Physical dependence alone doesn't establish opioid use disorder.
Some patients also develop increased pain sensitivity during long-term opioid treatment. Because these problems can overlap, the team should assess uncontrolled pain rather than automatically increasing medication.
Recovery risks deserve an honest discussion
The American Association of Hip and Knee Surgeons links preoperative opioid use with greater postoperative opioid needs and less favorable patient-reported outcomes. Its guidance also identifies associations with complications and continued opioid use after joint replacement.
These findings describe groups of patients; they don't predict your individual result. They do support planning earlier and discussing realistic expectations.
Tolerance to pain relief also doesn't eliminate the risk of slowed breathing or excessive sedation. Your overall health and other medicines still matter.
Coordinate Medication Decisions Before Surgery
Medication planning should begin before surgery day. During preoperative clearance for SuperPATH, ask how your orthopedic team will communicate with your opioid prescriber and anesthesia team.
Bring a complete medication history
Bring an updated list or photographs of your prescription labels. Include medicines taken occasionally, not only daily prescriptions.
Your team needs these details:
- Record each opioid's name, strength, formulation, and how often you actually take it.
- Include patches, long-acting products, and combination medicines containing acetaminophen.
- List sleep medicines, anxiety medicines, muscle relaxants, supplements, and alcohol or cannabis use.
- Provide your prescriber's contact information and describe previous problems with anesthesia or pain treatment.
Also explain whether opioids treat hip pain, back pain, nerve pain, or another condition. Replacing the hip may relieve arthritis pain without resolving every reason you need medication.
Discuss tapering without abrupt changes
The American Academy of Orthopaedic Surgeons reports better clinical outcomes among patients who reduce opioid use before hip replacement compared with those who continue unchanged. However, this doesn't establish one taper schedule for everyone.
If reduction is appropriate, your prescribing clinician should guide its timing and pace. Don't stop, skip, or change doses on your own.
Buprenorphine and methadone need advance coordination, especially when prescribed for opioid use disorder. Confirm the surgery-day instructions with your prescriber and anesthesiologist. A supervised plan should account for withdrawal prevention, ongoing treatment, and surgical pain.
Choose Anesthesia Around Your Health and Medication Use
Chronic opioid treatment doesn't determine whether you'll receive spinal or general anesthesia. The anesthesiologist considers your medical history, medication list, surgical needs, and previous anesthesia experiences.
Spinal anesthesia, sedation, and general anesthesia
Spinal anesthesia numbs the lower body. The team may pair it with sedation so you're relaxed or sleepy during surgery. General anesthesia makes you unconscious and requires airway management.
Both approaches can be appropriate. Blood thinners, spinal conditions, breathing problems, and other health factors can affect the choice.
Reviewing SuperPATH hip replacement anesthesia options can help you prepare for that conversation. However, your anesthesiologist must determine which approach fits you. Even with spinal anesthesia, you still need a plan for pain as the numbness wears off.
Breathing and alertness need separate attention
Tell the anesthesia team if you have sleep apnea, use CPAP, or have experienced severe sleepiness after medication. Also report lung disease and any past overdose or breathing difficulty.
Opioids can slow breathing, and sedatives can add to that effect. Benzodiazepines such as alprazolam or lorazepam deserve particular attention during medication review.
Your team may adjust sedation and postoperative monitoring based on these risks. Ask whether you should bring your CPAP equipment and whether overnight observation might be appropriate. Don't change anxiety or sleep medicines without the prescribing clinician's instructions.
Build Pain Control With More Than One Treatment
A multimodal plan combines treatments that work in different ways. For someone already taking opioids, the goal is to control pain while limiting unnecessary additional opioid exposure.
Nonopioid medicines and local pain relief
PROSPECT/ESRA hip-replacement guidance recommends acetaminophen with an NSAID or COX-2-selective medicine when medically appropriate. It also supports regional techniques that can reduce early postoperative pain.
These options require individual review. Kidney disease, stomach ulcers, bleeding risk, liver disease, and medication interactions can limit certain choices. Combination opioid products may already contain acetaminophen, so your team must account for the total amount.
The anesthesiologist may consider a regional nerve block, such as a PENG block. Your surgeon may also use local anesthetic around the surgical area. Ask how any temporary numbness or weakness could affect assisted walking.
Separate baseline treatment from surgical pain treatment
Your usual opioid regimen and any additional medicine for surgical pain need clearly defined roles. Otherwise, instructions can become confusing when you return home.
Ask which medicine addresses your established condition and which treats breakthrough surgical pain. The plan should explain dose limits, timing, and what to do if relief is inadequate.
Guidance that reserves opioids for rescue pain doesn't settle how to manage an existing long-term prescription. That requires coordination with your prescriber.
Ice, approved positioning, and paced activity also support comfort. They should complement prescribed treatment rather than replace necessary pain relief.
Set Recovery Goals Around Safe Movement
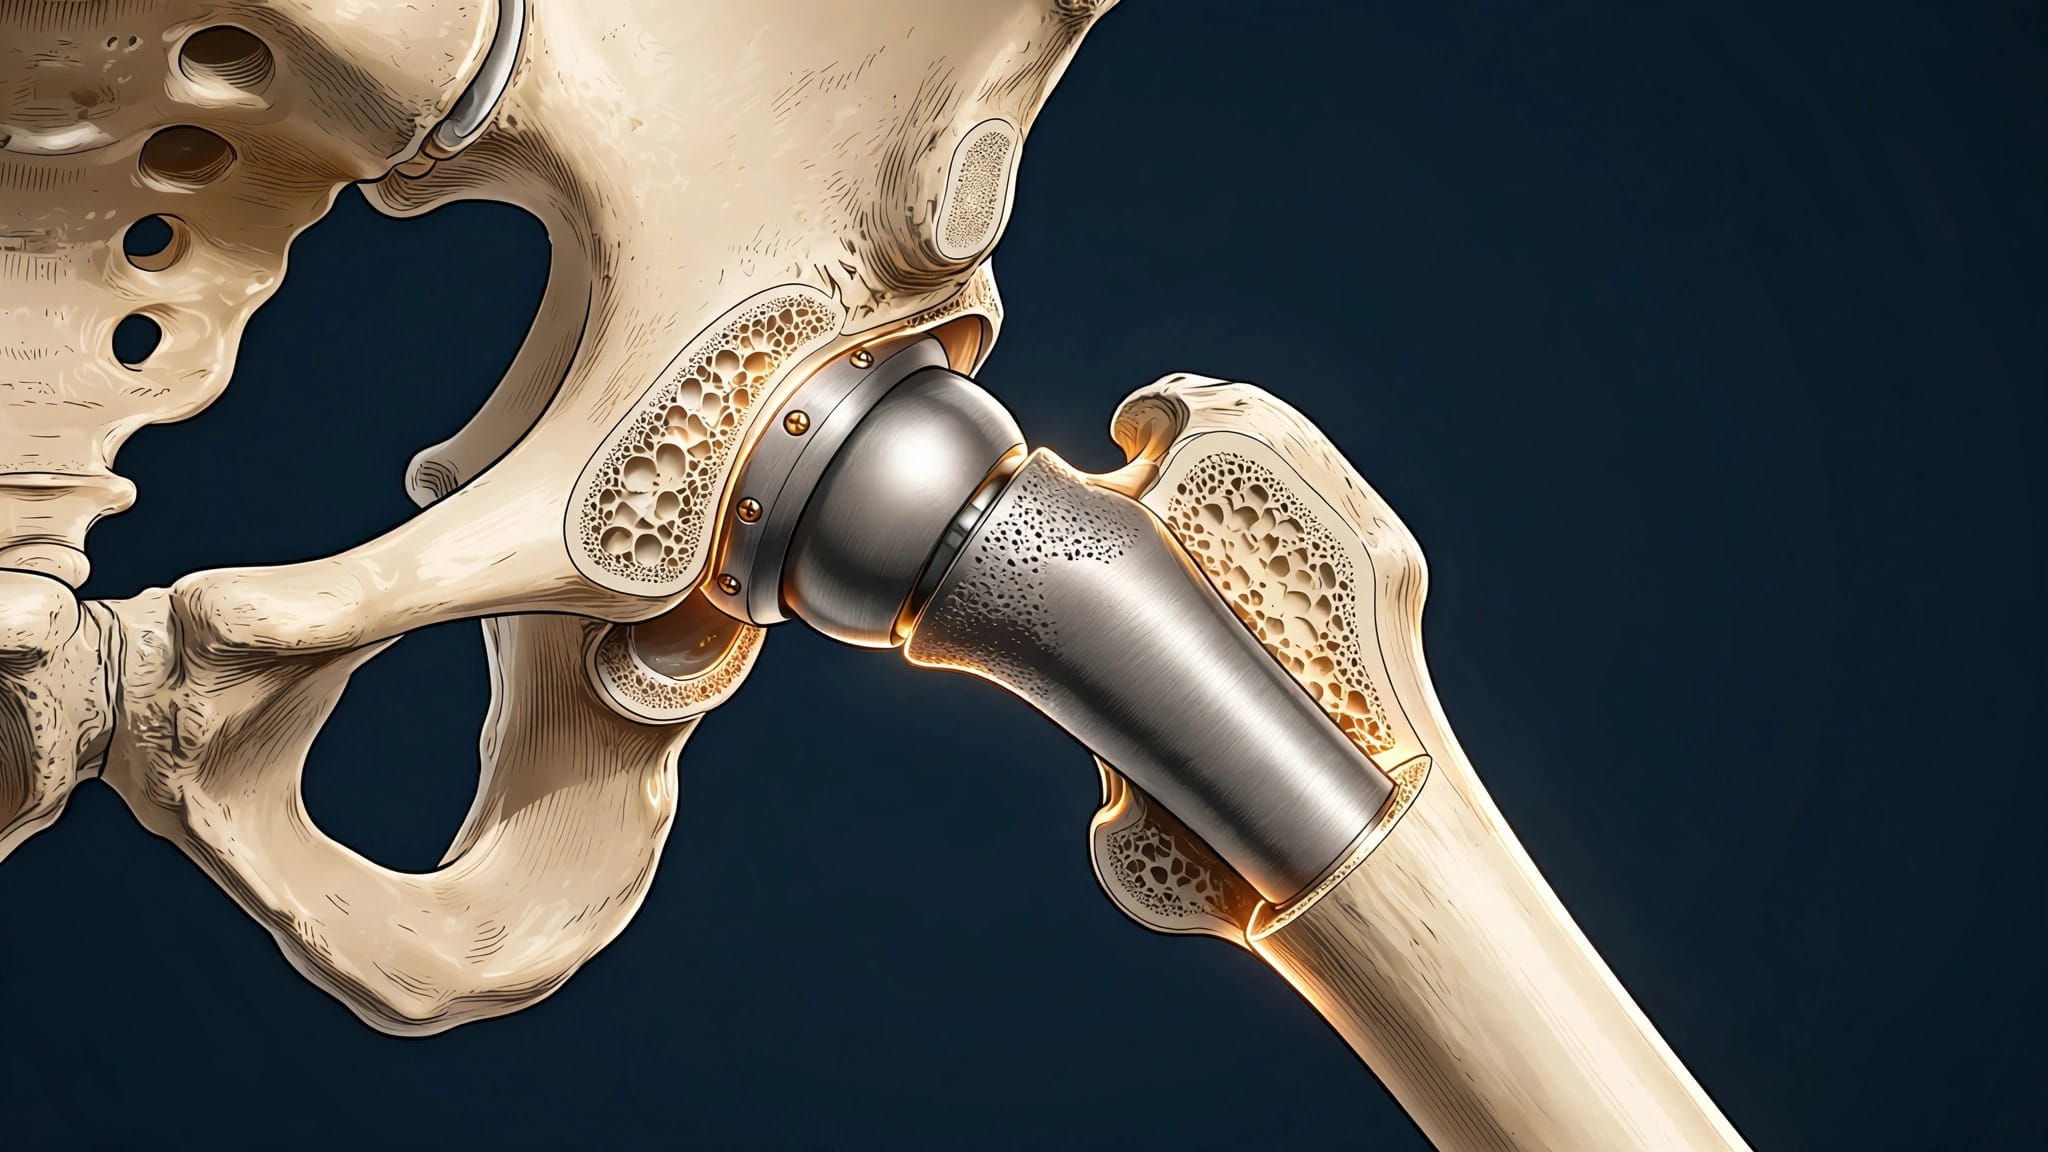
SuperPATH aims to limit disruption to surrounding muscles and soft tissue. However, hip replacement still involves bone preparation, implant placement, and healing. A smaller surgical approach doesn't make recovery painless.
During the first days, incision soreness, stiffness, and a deep ache may increase with standing or getting out of bed. Activity can cause temporary soreness, but the overall pattern should gradually improve.
For context, pain after SuperPATH hip replacement varies with health, baseline mobility, and the details of surgery. Someone taking opioids long term may follow a different medication timeline.
Function matters alongside pain scores. Tell your team whether you can sleep, transfer safely, and complete prescribed walking or exercises. These details help distinguish tolerable soreness from pain that blocks recovery.
Also report dizziness, nausea, or sleepiness that makes movement unsafe. Increasing medication may worsen those problems. The team can reassess the treatment balance instead.
Use your walker or cane as directed. Better pain relief doesn't mean the hip is ready for unrestricted activity, and physical therapy should follow your surgeon's weight-bearing instructions.
Make the Discharge Plan Clear Before Going Home
Some SuperPATH patients leave the same day; others need additional observation or therapy. Chronic opioid use doesn't automatically determine the length of stay. Pain control, breathing, alertness, mobility, and home support all influence the decision.
Assign responsibility for prescriptions and refills
Before discharge, identify who manages your established opioid prescription and who prescribes short-term surgical medication. Those clinicians should know what the other has ordered.
Get written instructions covering scheduled medicines, as-needed doses, and maximum amounts. Ask what to do if you vomit a dose, miss medication, or run short before follow-up. Don't improvise extra doses.
Also confirm whom to call after hours and when the first medication review will happen. Clear responsibility reduces the chance of duplicate prescriptions, conflicting directions, or an unplanned gap in treatment.
Plan a supervised return toward baseline
As surgical pain improves, your clinicians may reduce the additional postoperative opioid first. Returning to your preoperative regimen differs from eventually stopping long-term treatment.
The timing depends on pain, function, the original diagnosis, and your prescriber's plan. General advice about reducing pain medication after SuperPATH shouldn't become a self-directed taper.
Prepare home support as carefully as medication instructions. A caregiver can help track doses and notice unusual sleepiness. Ask about constipation prevention, nausea treatment, and secure storage. Avoid alcohol while taking postoperative opioids, and don't drive while medication impairs your alertness.
Know Which Symptoms Need Prompt Attention
Discuss naloxone before discharge. This opioid-overdose reversal medicine may be appropriate for home use, especially when breathing risks or sedating medications are present. Your caregiver should know where it is and how to use it.
Call 911 for slow or absent breathing, inability to wake, blue lips, chest pain, or severe shortness of breath. If opioid overdose is suspected, give naloxone as instructed while emergency help is on the way.
Contact the surgical team promptly for worsening pain, fever, wound drainage, calf swelling, or sudden difficulty bearing weight. Persistent vomiting, inability to urinate, or new confusion also needs medical attention.
Don't assume sweating or agitation means you need an extra opioid dose. Withdrawal, medication reactions, infection, and other problems can overlap. Describe the symptoms and your recent medication use so the team can guide you safely.
A Shared Plan Makes Recovery Safer
Chronic opioid use calls for coordinated care before and after SuperPATH surgery. Your surgeon, anesthesiologist, and opioid prescriber should agree on anesthesia, pain treatment, monitoring, and prescription responsibility.
Before surgery, confirm your medication instructions and discharge arrangements. Don't make opioid changes without your prescribing clinician's guidance.
The goal is manageable pain that supports safe movement while limiting medication-related harm. SuperPATH may offer a muscle-sparing approach, but your recovery plan must still fit your health and treatment history.
ADDITIONAL ARTICLES