October 12, 2026
Hip or Knee Surgery First? Planning Treatment for Both Joints
When both joints hurt, the question of hip or knee surgery first has no universal answer. The right order depends on which joint is causing the problem, how much each one limits daily life, and what the full examination shows.
Hip arthritis can sometimes cause pain felt in the knee, so the most painful area may not be the source. An orthopedic surgeon can compare symptoms, examination findings, imaging, and rehabilitation needs before recommending an individual plan.
Key Takeaways
- There is no single correct order for hip and knee surgery. The decision depends on the person and the condition of both joints.
- Hip arthritis can refer pain to the knee, so identifying the pain source comes before choosing a surgical plan.
- Pain severity, mobility, deformity, daily limitations, imaging, and recovery needs can all affect sequencing.
- X-rays provide useful information, but they don't make the decision on their own.
- The treating orthopedic surgeon should recommend an order based on the complete clinical picture.
Start by Identifying the Source of Pain
When the hip and knee both appear to be involved, diagnosis is the first step. Treating the wrong joint may leave the main source of pain unchanged.
Hip pain can show up near the knee
Hip arthritis may cause pain in the groin, outer thigh, or buttock, and some people feel discomfort farther down the leg. In some cases, pain that seems to come from the knee is referred from the hip. A careful exam helps distinguish hip arthritis and referred knee pain from a problem that begins in the knee itself.
Pain location offers clues, but it isn't a diagnosis by itself. Groin pain and reduced hip motion may point toward the hip, while knee tenderness or visible alignment changes can suggest a knee problem. Symptoms can overlap, and conditions in the lower back or sacroiliac joint may also affect how the leg feels.
Both joints may be contributing
A person can have arthritis in both joints, with each one causing separate symptoms. In that case, the surgeon needs to assess what each joint contributes to pain and limited movement. The question isn't only which area hurts more. It also matters whether the hip or knee is preventing walking, bending, sleeping, or managing routine activities.
Factors That Can Affect Surgical Order
The surgeon weighs several findings together rather than relying on one symptom or image. These details help show which joint needs attention sooner and what treatment could reasonably improve function.
Pain severity and daily limitations
Pain that interrupts sleep, makes dressing difficult, limits stair use, or shortens walking distance can indicate a substantial effect on daily life. The surgeon will consider how often the pain occurs, what movements trigger it, and whether it continues at rest.
Severity matters, but pain alone doesn't establish which operation should come first. For example, one joint may hurt more while the other causes a more serious walking or balance limitation. The full pattern, including what you can and can't do, gives the surgeon a clearer basis for planning.
Mobility, deformity, and stability
Restricted hip motion can change a person's walking pattern and make everyday movements harder. At the knee, deformity such as substantial bowing or knock-knee alignment, or a feeling that the joint is unstable, may affect function and surgical planning. Widespread cartilage loss or damage from an earlier injury can also matter when the surgeon evaluates knee replacement.
The importance of these findings depends on the individual case. A deformity on an image or a stiff joint on examination doesn't automatically decide the sequence. The surgeon considers whether it changes safe movement, places extra demands on the other joint, or affects rehabilitation.
What Imaging Can and Cannot Tell You
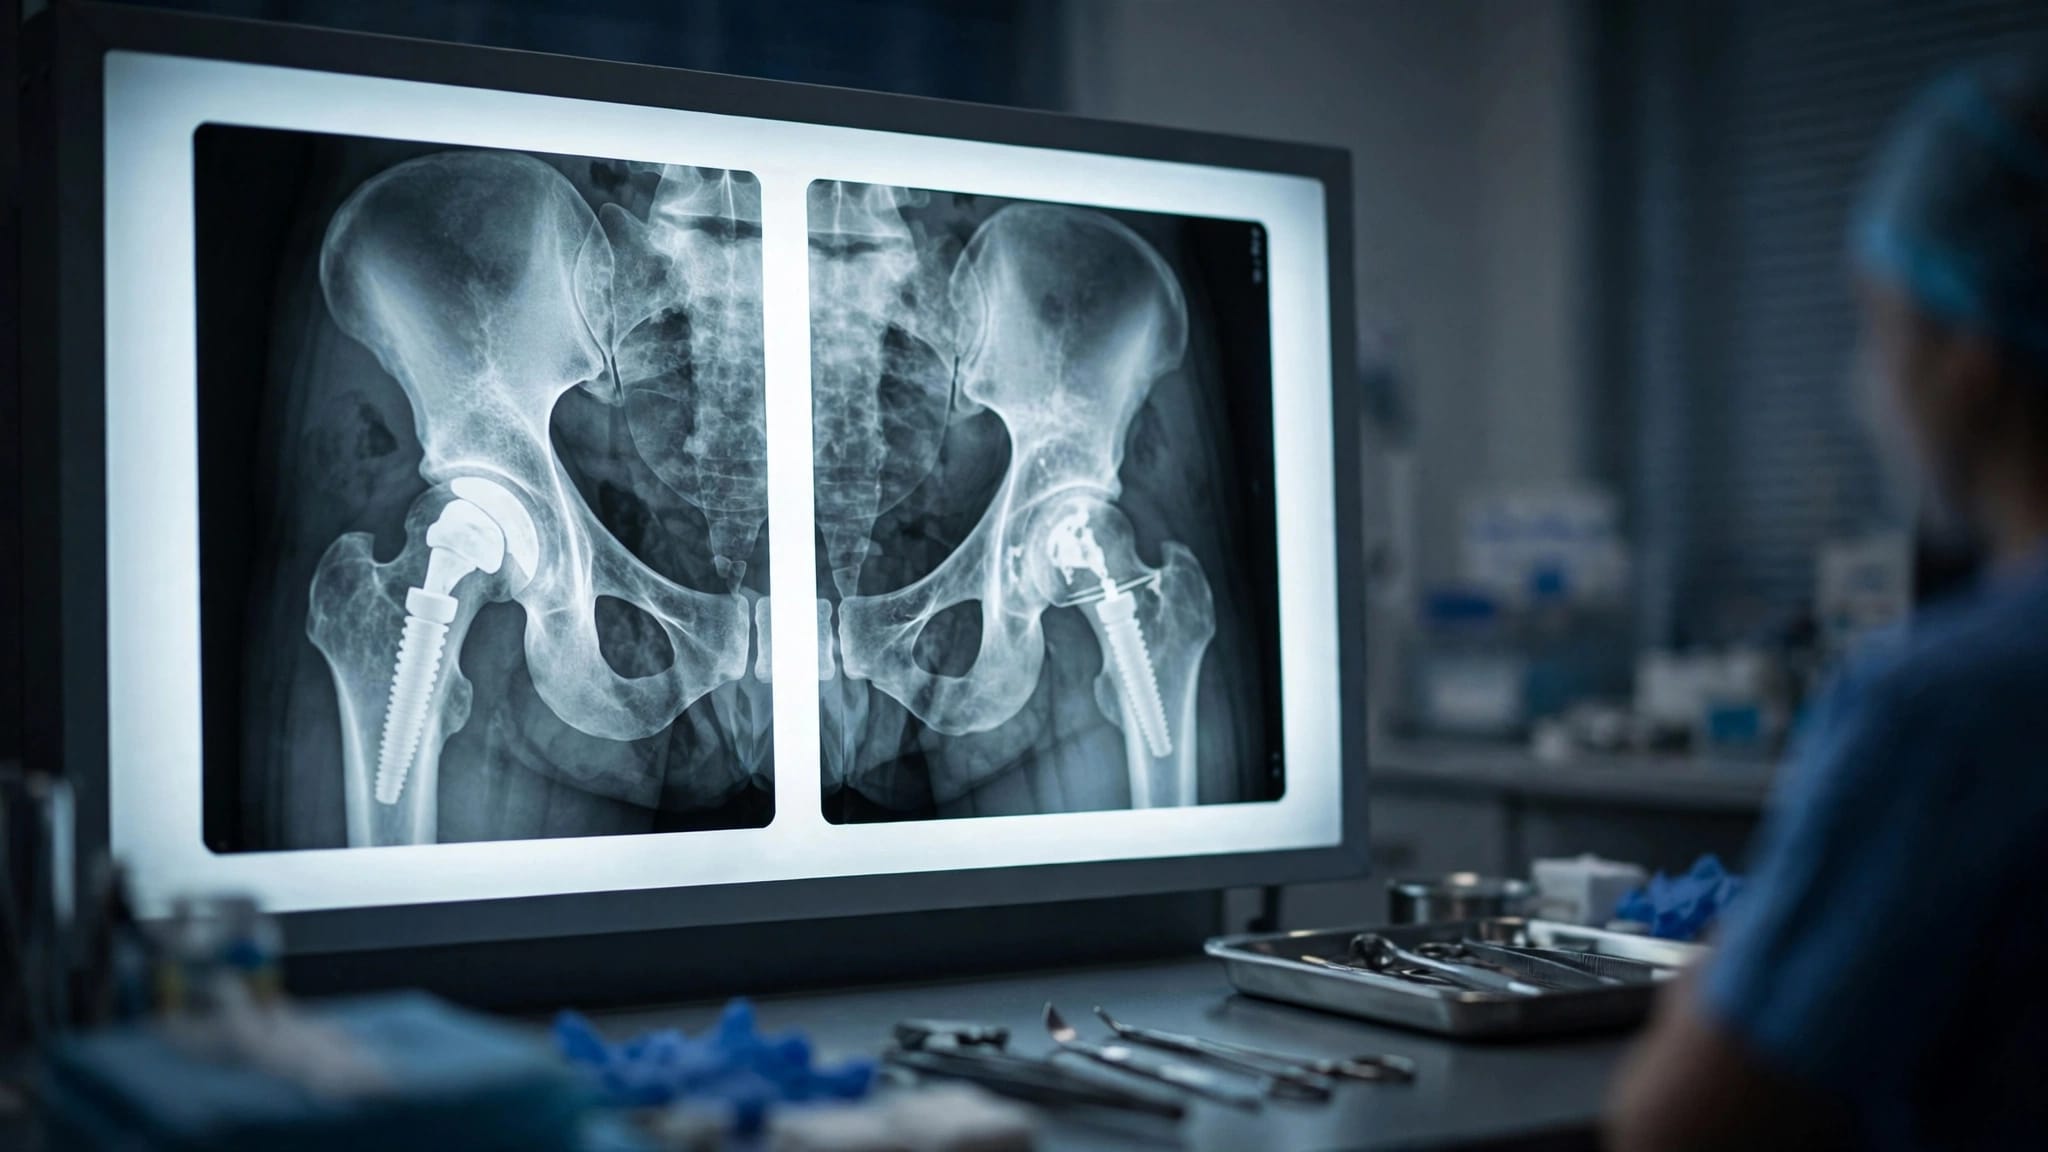
X-rays help show the structure of each joint. Hip and pelvis images may reveal joint-space loss, bone changes, or deformity. Knee images can show cartilage loss, alignment, and other signs of arthritis.
However, an image doesn't measure how much pain a person feels or how much a joint limits daily life. Some people have substantial changes on X-rays but manageable symptoms. Others have significant pain and loss of function that need further assessment, even when the images don't explain everything.
Your surgeon connects imaging with your symptoms, physical examination, walking pattern, and response to nonsurgical care. Physical therapy, activity changes, walking aids, medication, or injections may help manage arthritis for some people. If those measures no longer provide enough relief, hip arthritis treatment options can include discussing joint replacement when the symptoms and joint condition support it.
Rehabilitation Needs Belong in the Decision
Surgery is only one part of treatment. The plan also needs to account for how each joint affects movement and how the person may manage rehabilitation.
Consider how each joint affects movement
Walking and transfers rely on both hips and knees. If one joint is severely painful or stiff, it may limit the ability to move comfortably while the other joint recovers. The surgeon considers whether the first treatment could make daily movement easier or whether the untreated joint would remain a major barrier.
This is not a simple formula. Treating the most painful joint first may make sense in one situation, while another person's mobility limits or joint findings may point to a different plan. The surgeon's assessment should reflect how the specific combination of problems affects function.
Plan around the whole recovery
Rehabilitation can involve walking practice, exercises, and gradually returning to daily activities. The plan should account for strength, balance, the ability to use a walking aid if needed, and available support at home. A painful second joint may affect confidence or movement during recovery, so it deserves attention during preoperative planning.
Health conditions and medications can also influence preparation and recovery. If you have rheumatoid arthritis or another condition affecting several joints, discuss it with the orthopedic surgeon and the clinicians who manage it. These details can shape surgical and anesthesia planning.
Build a Plan Around Both Diagnoses
A useful surgical plan explains what each joint contributes, what treatment is expected to address, and how the order fits your needs. That can include discussing whether one joint is the primary pain source, how severe the damage is, and which symptoms are most limiting.
Review nonsurgical care and treatment goals
The surgeon may consider what you've already tried and whether those treatments helped. For hip arthritis, options can include physical therapy, activity adjustments, medication when appropriate, walking support, or an injection. A similar review of knee symptoms helps clarify whether surgery is being considered because pain and limitations persist despite other care.
Your goals also matter. Being able to sleep, walk farther, use stairs, or return to a daily activity may be more important than a change in an X-ray alone. Clear goals help connect the decision to practical outcomes.
Ask how the first procedure affects the next decision
If both joints may need surgery, ask the treating orthopedic surgeon to explain the reasoning behind the proposed order. Discuss how the first operation is expected to affect movement, what limitations may remain because of the other joint, and how progress will guide later care.
There is no need to apply a general rule to a situation that depends on individual findings. A good discussion should address both joints, not just the one scheduled for treatment first. At Ameglio Orthopedics, our care plans are individualized, and the treating surgeon can relate the options to your examination and imaging.
Understand the Recovery Demands
Recovery expectations may help with practical planning, but they don't determine which joint should be treated first. The experience varies by procedure and person, and recovery after one joint replacement can't predict the course of treatment for both joints.
For knee replacement, the procedure typically takes about 1 to 2 hours. Many patients walk with help the same day or the day after surgery, and many return home within 1 to 3 days. Some resume normal low-impact activities within 6 to 12 weeks, although individual recovery varies. Read about knee replacement surgery and its expected recovery, as well as the knee replacement recovery timeline.
The details of the knee procedure also depend on the condition of the joint. For example, widespread cartilage loss, substantial deformity, or instability may affect whether a total replacement is considered. Learn more about choosing the right type of knee replacement.
Frequently Asked Questions
Is there a standard rule to replace the hip before the knee?
No. There is no universally correct order. The surgeon considers which joint is causing symptoms, the severity of each problem, movement limitations, imaging, and the rehabilitation plan.
Can hip arthritis cause knee pain?
Yes. Hip arthritis can refer pain toward the knee, so knee-area pain doesn't always mean the knee is the source. An orthopedic evaluation helps distinguish referred pain from knee arthritis or another cause.
Can X-rays decide which joint needs surgery first?
No. X-rays show structural changes, but the surgeon also considers symptoms, physical examination, mobility, and response to nonsurgical care. Images are one part of the decision.
What should I discuss with the orthopedic surgeon?
Describe where the pain occurs, which activities are difficult, how your walking has changed, and what treatments you've tried. Ask how the findings in both joints affect the proposed order and recovery plan.
Conclusion
Choosing which joint to treat first depends on the whole clinical picture, not a universal hip-first or knee-first rule. Pain source, severity, mobility, deformity, imaging, and rehabilitation needs all help shape the decision.
A careful assessment can separate hip-related knee pain from problems in both joints. Work with your treating orthopedic surgeon to make a plan that fits your symptoms, examination, and goals.
ADDITIONAL ARTICLES