September 19, 2026
SuperPATH Hip Surgery With Coronary Stents: Questions to Ask
A coronary stent can affect when you safely have SuperPATH hip replacement. The timing of surgery, the type of stent, and your antiplatelet medicines all require a shared plan.
People with coronary stents who are considering SuperPATH usually want to know whether a minimally invasive hip procedure changes the cardiac rules. It does not. SuperPATH may limit disruption to some muscles and tissues, but it remains a total hip replacement with bleeding, clotting, anesthesia, and recovery considerations.
The best plan comes from your orthopedic surgeon, cardiologist, anesthesiologist, and primary care clinician reviewing the same information.
Why coronary stents change SuperPATH planning
A stent keeps a coronary artery open after a procedure called percutaneous coronary intervention, or PCI. The first weeks and months after placement can carry a higher risk of a clot forming inside the stent, especially if antiplatelet treatment is interrupted.
Hip replacement also creates bleeding concerns. Your team must balance the risk of stent thrombosis against bleeding around the new joint, wound problems, and anesthesia safety.
SuperPATH does not remove heart-related concerns
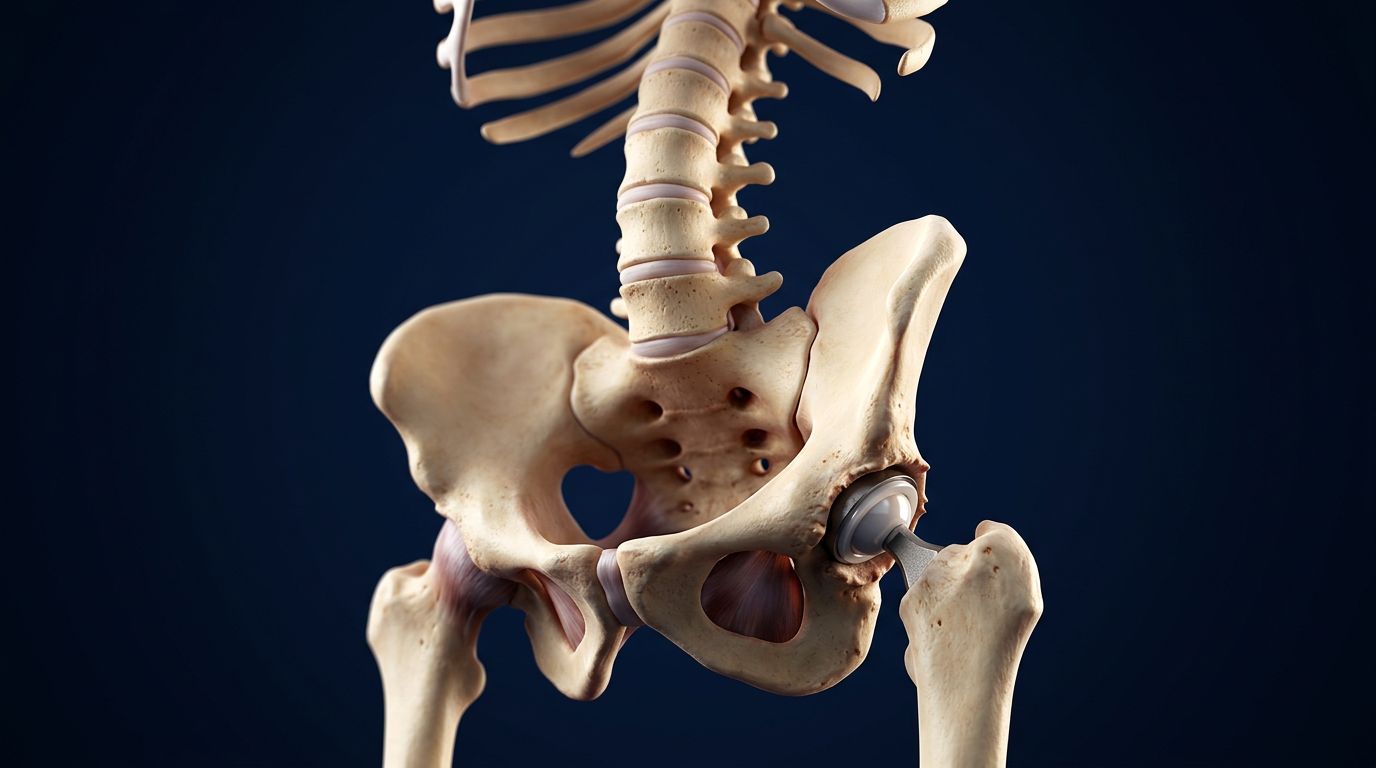
SuperPATH uses a tissue-sparing access route for total hip replacement. Some patients may walk earlier or experience less early muscle discomfort, but the approach does not make major surgery risk-free.
The operation still involves preparing the socket and femur, placing implants, and managing anesthesia. It can still cause bleeding, infection, blood clots, fracture, dislocation, or heart-related complications.
A smaller incision also does not mean you can schedule surgery immediately after PCI. The timing must reflect your cardiac history and the reason for stent placement.
The details of your PCI matter
Bring the date and records from your stent procedure if possible. Your team needs to know:
- Whether you received a bare-metal stent or drug-eluting stent
- Whether you had one stent or several
- Which artery was treated
- Whether PCI followed a heart attack or another acute coronary syndrome
- Which antiplatelet medicines you take
- Whether you have had chest pain, shortness of breath, or other symptoms since PCI
For additional context about coordinating cardiac conditions and hip surgery, review this guide to hip surgery and coronary stent medication planning.
Questions about when SuperPATH surgery can proceed
There is no single waiting period that applies to every patient. The recommended interval depends on the stent, the reason for PCI, your current heart health, and how urgent the hip replacement is.
How long ago was the stent placed?
For elective noncardiac surgery, current perioperative guidance generally recommends waiting at least 30 days after placement of a bare-metal stent.
A drug-eluting stent often requires more time. When the stent treated chronic coronary disease, waiting at least six months is generally preferred when practical. If PCI followed an acute coronary syndrome, the ideal delay may extend to 12 months.
The first three months after a drug-eluting stent deserve particular caution. Surgery during this period may be considered in some situations, but only after the cardiac and surgical teams compare the risks.
Ask your cardiologist, "What is the safest date for elective hip replacement based on my stent and heart condition?"
Is the hip problem urgent?
Severe arthritis can limit walking and sleep, but elective hip replacement usually allows time for medical optimization. A fracture, rapidly worsening function, or another urgent problem may change the discussion.
Your orthopedic surgeon should explain whether surgery can wait for a safer cardiac window. If postponing surgery is reasonable, that may allow more flexibility with antiplatelet treatment and anesthesia planning.
The question is not whether SuperPATH is minimally invasive. It is whether the operation can proceed safely at this point in your cardiac recovery.
Questions about aspirin and antiplatelet medicines
Many patients with coronary stents take aspirin plus a second antiplatelet drug. This combination is called dual antiplatelet therapy, or DAPT. These medicines reduce clotting inside the stent, but they can increase surgical bleeding.
Never stop, restart, or change one of these medicines on your own.
Should aspirin continue?
For many patients with prior PCI, low-dose aspirin, often 75 to 100 milligrams, is continued through surgery when the bleeding risk allows. That does not mean aspirin is automatically safe for every operation or every patient.
Your orthopedic surgeon and anesthesiologist must consider blood loss, wound drainage, the planned anesthetic, and your cardiac risk. The cardiologist should explain the danger of interrupting aspirin in your case.
Ask, "Should I continue aspirin on the day of surgery, and who will give me the final written instructions?"
Does the second antiplatelet drug need to pause?
Common P2Y12 inhibitors include clopidogrel, prasugrel, and ticagrelor. If your team decides that one must be interrupted, commonly cited platelet recovery intervals are approximately five days for clopidogrel, seven days for prasugrel, and three days for ticagrelor.
These are planning intervals, not personal instructions. Your cardiologist may advise continuing treatment if the risk of stent thrombosis is high. In general, DAPT is especially important when surgery occurs within 30 days of a bare-metal stent or within three months of a drug-eluting stent, unless bleeding risk clearly outweighs the protection.
Ask when the medicine should stop, who will authorize the change, and when it should restart after surgery. For a broader medication review, see these instructions about medications to stop before SuperPATH hip replacement.
Questions for each member of your surgical team
A safe plan can fail if one clinician does not know what another has recommended. Ask the office to place the cardiology, orthopedic, anesthesia, and primary care instructions in the same record.
What should the cardiologist clarify?
Ask your cardiologist:
- Is my heart condition stable enough for elective hip replacement?
- What is my stent type, placement date, and thrombosis risk?
- How long should I remain on DAPT?
- Can aspirin continue during surgery?
- If another antiplatelet drug must pause, what exact dates apply?
- When should treatment restart after surgery?
- Do I need additional testing or a recent cardiac evaluation?
A cardiologist may also identify symptoms that should delay surgery, such as new chest pressure, worsening breathlessness, fainting, or a change in exercise tolerance.
What should the orthopedic surgeon and anesthesiologist clarify?
Ask the orthopedic surgeon how the stent and medication plan affect the planned SuperPATH procedure, expected blood loss, recovery setting, and clot prevention.
Ask the anesthesiologist whether spinal anesthesia, general anesthesia, or another approach is appropriate. Spinal anesthesia is common for some hip replacements, but antiplatelet treatment can affect whether neuraxial anesthesia is safe. The anesthesiologist must review your actual medicines and timing.
You can also read this overview of anesthesia for SuperPATH hip replacement.
Your primary care clinician can help review blood pressure, diabetes, anemia, kidney function, smoking, sleep apnea, and other conditions that may affect healing or recovery.
Preparing for a coordinated consultation
Bring a complete medication list to every appointment. Include prescription drugs, aspirin, over-the-counter pain relievers, vitamins, supplements, injections, inhalers, and medicines prescribed by other specialists.
Write down the date of your PCI and the names of your stents if you have them. Bring recent cardiology notes, catheterization reports, test results, and the contact information for your cardiologist.
A preoperative clearance visit can identify issues involving anesthesia, healing, medication timing, and early movement. This SuperPATH hip replacement preoperative clearance guide can help you organize questions before the visit.
Build one written medication plan
Your instructions should state:
- Which medicines to take on the morning of surgery
- Which medicines to continue after surgery
- Whether and when an antiplatelet drug pauses
- Who gives permission to restart it
- What to do if surgery is postponed
- Which symptoms require an urgent call
Verbal instructions can be misunderstood, especially when several offices are involved. Ask for written directions and confirm that each clinician agrees with them.
Discuss recovery and clot prevention
Hip replacement increases the risk of blood clots because surgery and temporary reduced mobility affect circulation. Your team may use walking, compression devices, and medication-based prevention.
That plan must account for your coronary medicines. Do not assume that your usual antiplatelet treatment replaces the clot-prevention plan prescribed after hip replacement. Ask what medication, dose, and duration are appropriate for you.
When to contact the team before surgery
Tell your cardiologist and orthopedic office promptly if you develop new or worsening chest pain, shortness of breath, fainting, racing or irregular heartbeat, or a sudden decline in exercise tolerance.
Also report a recent emergency visit, hospitalization, abnormal cardiac test, infection, fall, or change in medication. These events may affect whether surgery should proceed as planned.
After surgery, seek urgent help for severe chest pressure, trouble breathing, fainting, sudden weakness, uncontrolled bleeding, or a rapidly worsening wound. Follow the discharge instructions for less urgent concerns, such as increasing swelling, drainage, fever, or pain.
FAQ about SuperPATH and coronary stents
Can I have SuperPATH hip replacement after a coronary stent?
Many patients can have hip replacement after PCI, but the timing and medication plan must be individualized. Your stent type, placement date, reason for PCI, heart stability, and bleeding risk all matter.
Is SuperPATH safer than another hip approach for someone with a stent?
SuperPATH may reduce disruption to certain tissues, but it does not eliminate the cardiac risks of hip replacement. Current evidence does not support using the approach alone to bypass recommended surgical timing or antiplatelet precautions.
The safest approach is the one your surgeon can perform effectively for your anatomy and medical condition.
Can I stop clopidogrel before surgery?
Only your cardiologist and surgical team should decide that. Stopping clopidogrel too soon can increase the risk of stent thrombosis. Continuing it may increase bleeding, so the decision requires coordination with the anesthesiologist and orthopedic surgeon.
What if my hip pain is severe while I wait?
Ask whether nonsurgical treatment can help you remain mobile during the recommended waiting period. Your orthopedic surgeon can also explain how urgent the operation is and whether another treatment is appropriate while your heart team completes its review.
Educational information cannot replace individualized medical advice. Do not stop or change aspirin, clopidogrel, prasugrel, ticagrelor, or any other medicine without instructions from your cardiologist and surgical team.
A safer plan starts with one shared decision
A coronary stent does not automatically prevent SuperPATH hip replacement, but it makes timing and medication planning essential. The strongest plan accounts for the stent procedure, your current heart health, the bleeding risk of surgery, and the anesthesia approach.
Bring your records, request written instructions, and make sure your orthopedic surgeon, cardiologist, anesthesiologist, and primary care clinician agree on the plan. That coordination gives you a clearer path toward hip surgery and a safer recovery.
ADDITIONAL ARTICLES